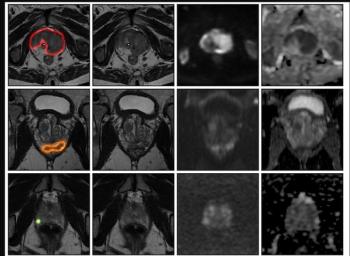
An AI model for prostate MRI offered an 89 percent AUC for prostate cancer detection in external validation testing, according to a newly published international multicenter study.
Case History: 3-month-old child with abnormal growth of head size.
Case History: A 3-month-old child brought by parents with complaints of abnormal growth of head size. As the patient’s appearance and head size was not normal, a detailed family and medical history was taken. Review of medical history was unremarkable. The mother reported normal labor and delivery. There were no anomalies in any siblings or near relatives. On general examination, the patient was had a wide nasal bridge, hypertelorism, and exophthalmos. Intra oral examination revealed high arch palate, hypo plastic maxilla causing prognathism of the mandible. The patient was subjected to radiographic investigations.
Lateral skull view demonstrated a scaphocephaly skull, retruded maxilla with a relatively large mandible and copper beaten appearance (Figure 1). Radiographic examination of metacarpal bones and fingers were unremarkable. Further, on non contrast CT, brain and face was performed, which revealed increased antero-posterior diameter of the skull with obliterated sagittal suture (scaphocephaly skull), small paranasal sinuses (Figure 2). Three-dimensional (3D) computed tomographic images of the skull revealed increased circumference of the skull in antero-posterior diameter with hypo plastic maxilla (Figure 3). On non contrast MRI and CT, brain did not reveal any abnormality in brain parenchyma. No evidence of hydrocephalous was noted (Figure 4).
[[{"type":"media","view_mode":"media_crop","fid":"27332","attributes":{"alt":"","class":"media-image","id":"media_crop_971060955983","media_crop_h":"0","media_crop_image_style":"-1","media_crop_instance":"2636","media_crop_rotate":"0","media_crop_scale_h":"0","media_crop_scale_w":"0","media_crop_w":"0","media_crop_x":"0","media_crop_y":"0","title":" ","typeof":"foaf:Image"}}]]
Figure 1. Lateral skull projection reveals abnormally enlarged skull (more antero-posterior diameter) due to premature closure of sagittal suture (scaphocephaly) mandibular prognathism (white arrow), maxillary hypoplasia (arrow), copper beaten appearance and enlarged hypophyseal cavity.
[[{"type":"media","view_mode":"media_crop","fid":"27333","attributes":{"alt":"","class":"media-image","id":"media_crop_8803275623164","media_crop_h":"0","media_crop_image_style":"-1","media_crop_instance":"2637","media_crop_rotate":"0","media_crop_scale_h":"0","media_crop_scale_w":"0","media_crop_w":"0","media_crop_x":"0","media_crop_y":"0","title":" ","typeof":"foaf:Image"}}]]
Figure 2. Non contrast CT of brain and face bone window images (A and B) show increased antero-posterior diameter of skull (scaphocephaly skull), copper beaten appearance, small paranasal sinuses, mandibular prognathism. C and D show maxillary hypoplasia (arrow). E shows premature closure of sagittal suture in its posterior aspect (small arrow) resultant scaphocephaly.
[[{"type":"media","view_mode":"media_crop","fid":"27334","attributes":{"alt":"","class":"media-image","id":"media_crop_5760550229278","media_crop_h":"0","media_crop_image_style":"-1","media_crop_instance":"2638","media_crop_rotate":"0","media_crop_scale_h":"0","media_crop_scale_w":"0","media_crop_w":"0","media_crop_x":"0","media_crop_y":"0","title":" ","typeof":"foaf:Image"}}]]
Figure 3. Three-dimensional (3D) computed tomographic VR images (A and B) of the skull with face revealed increased circumference of the skull in antero-posterior diameter.
[[{"type":"media","view_mode":"media_crop","fid":"27335","attributes":{"alt":"","class":"media-image","id":"media_crop_9428201503493","media_crop_h":"0","media_crop_image_style":"-1","media_crop_instance":"2639","media_crop_rotate":"0","media_crop_scale_h":"0","media_crop_scale_w":"0","media_crop_w":"0","media_crop_x":"0","media_crop_y":"0","title":" ","typeof":"foaf:Image"}}]]
Figure 4. Non contrast CT brain (A, axial and B, coronal) images and non contrast MRI (C, T2WI axial, D, sagittal and FLAIR, coronal E and axial F) images show normal brain parenchyma. No evidence of hydrocephalus is noted.
Diagnosis: Crouzon syndrome
Discussion: Crouzon syndrome (CS) is a rare genetic disorder characterized by premature closure of one or more cranial sutures and produces characteristic craniofacial and other associated abnormalities. It is characterized by premature craniosynostoses, mid facial hypoplasia and orbital defects. Here, we report a case of this rare entity. The patient presented with brachycephaly and abnormal calvarial shape. Severe cases can give a "cloverleaf skull," maxillary hypoplasia, exophthalmos, mandibular prognathism or bifid uvula along with dental and orbital abnormalities.
Genetics: It carries an autosomal dominant inheritance due to a mutation in fibroblast growth factor receptor 2 (FGFR2) gene on chromosome 10q25-26.
Associations:
References
1. Chen CP, Lin SP, Su YN, et al. A cloverleaf skull associated with Crouzon syndrome. Arch Dis Child Fetal Neonatal Ed. 2006;9:F98.
2. Entezami M, Albig M, Knoll U, et al. Ultrasound Diagnosis of Fetal Anomalies. Thieme. 2003.
3. Lowe LH, Booth TN, Joglar JM, et al. Midface anomalies in children. Radiographics. 20:907-922.
4. Altintas AG, Gül aksoy FG, Altintas CS, et al. Evaluation of findings in Crouzon's syndrome. Orbit. 1999;18:247-259.