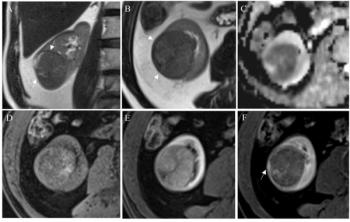
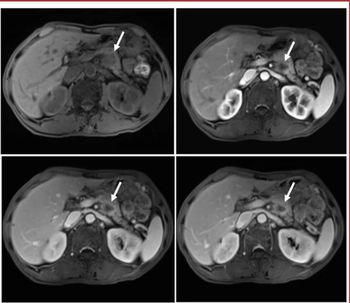
“Growing evidence supports the potential of imaging techniques, particularly contrast-enhanced MRI, to profile HCC aggressiveness (eg, pathologic subtypes, microvascular invasion) … and prognosis (eg, postoperative recurrence, extrahepatic metastases),” wrote lead study author Hanyu Jiang, M.D., who is affiliated with the Department of Radiology at the West China Hospital and Sichuan University in Chengdu, China, and colleagues.
The study authors noted a key finding from the study was less than 50 percent APHE on MRI being predictive of advanced recurrence of HCC.
“Hypoenhancing areas at imaging may represent intratumoral necrosis, fibrotic stroma, and/or hemorrhage in histopathologic specimens, all of which have been associated with unfavorable prognosis in HCC,” pointed out Jiang and colleagues. “Additionally, less than 50% APHE has been previously associated with macrotrabecular-massive HCC, a pathologic subtype linked to increased metastasis and poorer survival.”
Three Key Takeaways
- ASRAR scoring model. The ASRAR (Advanced-Stage Recurrence after Resection) score, calculated based on a combination of serum neutrophil count, tumor size, and MRI arterial phase hyperenhancement proportion, offers an advanced and effective risk stratification tool for HCC patients who have undergone curative-intent resection procedures.
- Improved predictive accuracy. The ASRAR score demonstrated superior predictive accuracy for advanced-stage HCC recurrence compared to existing staging systems, with a two-year concordance index (C-index) of 82% and a time-dependent area under the receiver operating characteristic curve (AUC) of 82%. This score outperformed other staging systems such as BCLC and AJCC.
- Potential for adjuvant therapy for high-risk patients. The ASRAR score can aid in individualized prognostication and the selection of adjuvant therapy for HCC patients identified as being at high-risk for recurrence based on the ASRAR score. Patients with high-risk scores who received adjunctive therapy had significantly longer median recurrence-free survival compared to those who did not receive adjunctive therapy, suggesting its potential utility in treatment decision-making.
While the researchers noted a lack of standardization and approved indications for the use of adjunctive therapy in the treatment of HCC, they noted that risk stratification with the ASRAR scoring model demonstrated considerable benefit with adjunctive therapy for patients deemed to be at high risk for HCC recurrence. Specifically, they found the use of adjunctive therapy in this patient population was associated with more than triple the median recurrence-free survival (22.9 months) of high-risk patients who did not have adjunctive therapy (7.2 months).
“These results suggest that the ASRAR score may serve as a decision-making tool for individualized prognostication and adjuvant therapy selection,” added Jiang and colleagues.
(Editor’s note: For related content, see “Meta-Analysis Assesses Impact of Radiomics for Predicting Hepatocellular Carcinoma Recurrence,” “Can a CT Radiomics Model Improve Risk Assessment for Macrotrabecular-Massive Hepatocellular Carcinoma?” and “Microvascular Invasion in Hepatocellular Carcinoma: Can a CT Radiomics Model Have an Impact?”)
Beyond the inherent limitations of a retrospective single-center study, the researchers noted that pervasive chronic hepatitis B, affecting 97.8 percent of the study cohort, limits extrapolation of the study findings to those without hepatitis B. The study authors also acknowledged that individualized use of adjuvant therapies, more commonly utilized late during the study period, may also impact application of study results to broader populations. Given that the ASRAR score was developed in patients who had surgical resection, the researchers conceded that it may not be useful in assessing patients undergoing liver transplantation.