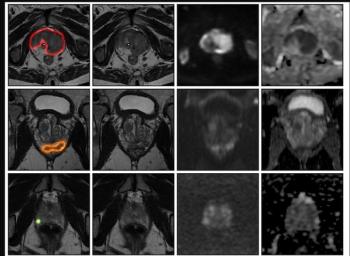
“Our simulation suggests a synergistic relationship between interpretation by radiologist and AI predictions, where their combined effectiveness surpasses individual contributions, particularly for PI-RADS category 3 lesions. This combined approach may be instrumental in improving the classification of these indeterminate lesions,” wrote lead study author Mason J. Belue, M.D., who is affiliated with the Department of Urology at the University of Arkansas for Medical Sciences in Little Rock, Ark., and colleagues.
Three Key Takeaways
1. AI matches radiologists in PCa detection. The deep learning algorithm demonstrated comparable sensitivity to radiologists in detecting both overall prostate cancer (PCa) and clinically significant PCa (csPCa) on biparametric MRI, supporting its potential role in clinical diagnostics.
2. AI enhances PI-RADS 3 lesion classification. The combination of AI and radiologist interpretation led to the reclassification of many PI-RADS 3 lesions to higher-risk categories, improving diagnostic precision and potentially reducing unnecessary biopsies.
3. AI aids detection in MRI-negative patients. The algorithm showed strong performance in identifying csPCa among patients with PI-RADS 1–2 lesions and elevated PSA levels — detecting 100 percent of csPCa cases in this subgroup — suggesting added value in patients with negative imaging but high clinical suspicion.
The researchers noted that 35 patients in the cohort with normal findings on prostate MRI proceeded to systematic biopsy due to significantly high or persistently elevated prostate-specific antigen (PSA) levels, which is in line with prostate cancer guidelines from the National Comprehensive Cancer Network (NCCN), the American Urological Association (AUA) and the Society of Urologic Oncology (SUO). Pointing out that approximately one-third of this sub-cohort had csPCa, the study authors suggested the AI algorithm would have been advantageous for these patients.
“Our study demonstrated that 78% of these csPCa cases could have been predicted with use of this AI algorithm. Remarkably, among 20 patients who had PI-RADS 1–2 lesions per MRI, AI would have detected 83% of PCa and 100% of csPCa,” pointed out Belue and colleagues.
(Editor’s note: For related content, see “AI and bpMRI for csPCa Detection: What a New Meta-Analysis Reveals,” “Meta-Analysis Shows No Difference Between bpMRI and mpMRI in Ruling Out csPCa” and “Can Deep Learning Ultra-Fast bpMRI Have an Impact in Prostate Cancer Imaging?”)
Beyond the inherent limitations of a single-center retrospective study, the authors acknowledged the small cohort size. They also pointed out that the PCa prevalence in study participants with PI-RADS 1-3 may have resulted from the inclusion of patients on active surveillance and opting for biopsy in cases involving high-risk features for PCa even if they had a negative MRI exam.