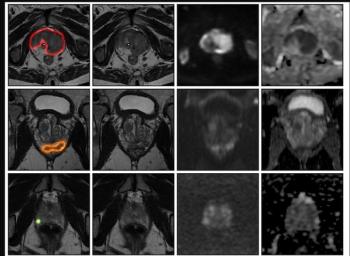
“Implementation of the most recent PI-RADS update did not improve the incongruence in PCa grade assessment between Tbx and surgery,” wrote study co-author Baris Turkbey, M.D., a senior clinician and radiologist at the National Cancer Institute and the National Institutes of Health in Rockville, Md., and colleagues.
The researchers saw similar concordance rates between Tbx and radical prostatectomy for both cohorts (57 percent for PI-RADS 2.1 vs. 51 percent for PI-RADS 2.0). Turkbey and colleagues also noted similar concordance rates in grade group 2 (GG2) patients and GG3 patients (57 percent for PI-RADS 2.1 vs. 53 percent for PI-RADS 2.0).
Three Key Takeaways
- Limited impact of PI-RADS 2.1 update. The study suggests that the updated PI-RADS 2.1 classification for prostate cancer assessment on MRI does not significantly differ from the previous PI-RADS 2.0, indicating that the newer version may not offer substantial improvements in clinical evaluation.
- Grading consistency. The research found that both PI-RADS 2.0 and PI-RADS 2.1 exhibited similar rates of upgrading and downgrading of prostate cancer assessments on MRI. This suggests that the choice between these two versions may not significantly affect the accuracy of grading prostate cancer.
- Importance of GG2 and GG3 Differentiation. The study authors discuss the importance of distinguishing between grade group 2 (GG2) and grade group 3 (GG3) in cases of clinically significant prostate cancer. Accurate grading is crucial as it can impact treatment decisions, with GG3 potentially shifting patients from favorable intermediate risk to unfavorable intermediate risk categories according to NCCN guidelines, potentially requiring more aggressive management.
Turkbey and colleagues emphasized the importance of being able to distinguish between GG2 and GG3 in cases of clinically significant prostate cancer (csPCa).
“ … The presence of GG3 may change the patient’s risk category from favorable intermediate risk to unfavorable intermediate risk per (National Comprehensive Cancer Network (NCCN) guidelines,” noted Turkbey and colleagues. “In patients with favorable intermediate risk, active surveillance may remain a management option; however, unfavorable intermediate risk usually requires active treatment with surgical intervention or radiotherapy.”
(Editor’s note: For related content, see “Study: ‘All Men with PSAs Between 3 and 20 ng/mL Should Undergo MRI Before Biopsy’,” “Study: Combination of Ultrasound and MRI-Targeted Biopsy Enhances Detection of Prostate Cancer” and “Study Says AI Mapping More Effective than MRI for Assessing Extent of Prostate Cancer.”)
In regard to study limitations, the researchers conceded that review of all MRI images in the study by one genitourinary radiologist and a small number of patients with PI-RADS categories 2 or 3 may limit broader extrapolation of the study findings. The study authors also acknowledged possible selection bias with the cohort being limited to patients who underwent radical prostatectomy.
(Editor's note: For the latest news and research on prostate cancer imaging, click here.)