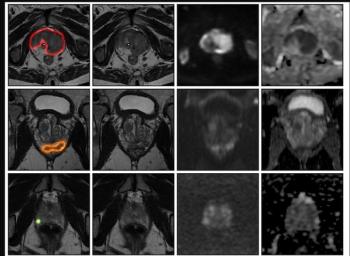
In the aforementioned 400-case subset, the study authors found the AL model had a superior positive predictive value (PPV) (68 percent vs. 53.2 percent) and a higher negative predictive value (NPV) (93.8 percent vs. 90.2 percent) in comparison to radiologists. However, when utilizing a PI-RADS 3 or greater operating point in the entire 1,000-case testing cohort, the researchers noted that radiologists had comparable PPVs (60.6 percent vs. 60.5 percent) and NPVs (97.3 percent vs. 97.3 percent) to the AI model.1
Three Key Takeaways
1. Higher diagnostic accuracy. The AI system demonstrated a higher area under the receiver operating characteristic curve (AUROC) of 91 percent, compared to the pooled AUROC of 86 percent for the 62 radiologists. This indicates that the AI system is more accurate in distinguishing between patients with and without csPCa.
2. Reduction in false positives. The AI model achieved 50.4 percent fewer false positive results at the same specificity compared to radiologists. This reduction in false positives can decrease unnecessary follow-up procedures and patient anxiety.
3. Improved predictive values. In a subset of 400 MRI exams, the AI system had a superior positive predictive value (PPV) of 68 percent versus 53.2 percent for radiologists, and a higher negative predictive value (NPV) of 93.8 percent compared to 90.2 percent for radiologists. These improved predictive values suggest that the AI model is better at correctly identifying both the presence and absence of csPCa.
“We hypothesize that this difference in performance between the radiologists participating in the reader study and the radiologists reporting in practice was due to those reporting in practice having access to patient history (including previous prostate-specific antigen levels and imaging and biopsy outcomes), peer consultation (or multidisciplinary team meetings), and protocol familiarity,” added Saha and colleagues.
In comparison to radiologist interpretation of multiparametric prostate MRI in the PROMIS study, the researchers said the AI model offered a 34 percent higher specificity rate (45 percent vs. 79.1 percent) and over a 17 percent higher NPV (76 percent vs. 93.8 percent) at similar sensitivity rates (88 percent vs. 89.5 percent).1,2
(Editor’s note: For related content, see “Study: Adjunctive AI Imaging Software Enhances Contouring of Prostate Cancer,” “Researchers Unveil PI-QUAL v2 for Prostate MRI Quality Assessments” and “Study: PSMA PET/CT Agent May Rule Out 93 Percent of PI-RADS 3 Lesions.”)
In regard to study limitations, the authors acknowledged that over 93 percent of the reviewed MRI exams were performed with one MRI device manufacturer. They also noted that reviewing radiologist assessments were provided in a controlled, online reading environment as opposed to native workstations.
References
1. Saha A, Bosma JS, Twilt JJ, et al. Artificial intelligence and radiologists in prostate cancer detection on MRI (PI-CAI): an international, paired, non-inferiority, confirmatory study. Lancet Oncol. 2024 Jun 11:S1470-2045(24)00220-1. Doi: 10.1016/S1470-2045(24)00220-1. Online ahead of print.
2. Ahmed HU, El-Shater AB, Brown LC, et al. Diagnostic accuracy of multi-parametric MRI and TRUS biopsy in prostate cancer (PROMIS): a paired validating confirmatory study. Lancet. 2017;389(10071):815-822.