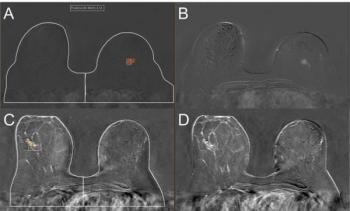
“ … The degree of background parenchymal enhancement (BPE) has an impact on the diagnostic performance of breast MRI, with minimal or mild BPE being associated with higher sensitivity and specificity and moderate or marked BPE being associated with lower diagnostic performance. The degree of BPE in MRI reports may prompt follow-up strategies and additional imaging to prevent missed diagnoses and unnecessary biopsies,” wrote Sonja Bechyna, M.D., and Pascal A.T. Baltzer, M.D., who are affiliated with the Department of Biomedical Imaging and Image-Guided Treatment at the University of Vienna in Vienna, Austria, and colleagues.
While acknowledging that they did not specifically assess the impact of BPE on abnormal interpretation rate or biopsies, the study authors emphasized key treatment considerations that can be missed in cases involving a higher degree of BPE.
“Moderate or marked BPE may mask multifocal or multicentric lesions, especially non-mass enhancements, compared with monofocal masses,” noted Drs. Bechyna and Baltzer.
Three Key Takeaways
1. Higher BPE reduces diagnostic accuracy. Breast MRIs with moderate or marked background parenchymal enhancement (BPE) show lower sensitivity (84.1 percent) and specificity (78.7 percent) compared to those with minimal or mild BPE (sensitivity 95.3 percent, specificity 89 percent).
2. Implications for lesion detection. Moderate or marked BPE may mask multifocal or multicentric lesions, especially non-mass enhancements, potentially leading to missed diagnoses.
3. Role in personalized risk stratification. BPE could be integrated into risk models to tailor imaging surveillance and patient counseling, and may serve as a surrogate marker for treatment response in some settings.
In an accompanying editorial, Manisha Bahl, MD, suggested that BPE could be a factor in enhancing personalized risk stratification.
“BPE could be added to risk models to guide imaging surveillance strategies and inform individualized patient counseling. In addition, changes in BPE have been explored as a surrogate marker of response to neoadjuvant chemotherapy. These emerging insights about BPE highlight the need for more standardized and reproducible methods for assessing BPE in addition to a clearer understanding of its biologic underpinnings,” posited Dr. Bahl, an associate professor of radiology at Harvard Medical School.
(Editor’s note: For related content, see “Study Questions Utility of Ultrafast Breast MRI for Challenging Lesions and Moderate/Marked BPE,” “Contrast-Enhanced Mammography Study Reveals 24 Percent Lower Sensitivity with Moderate/Marked BPE” and “Abbreviated MRI and Contrast-Enhanced Mammography Provide Fourfold Higher Cancer Detection than Breast Ultrasound.”)
In regard to study limitations, the meta-analysis authors noted that single-center studies comprised many of the reviewed studies and acknowledged a lack of differentiation between mass and non-mass lesions with different BPE in the majority of the studies. The researchers also conceded wide variability between the studies with respect to screening indications.