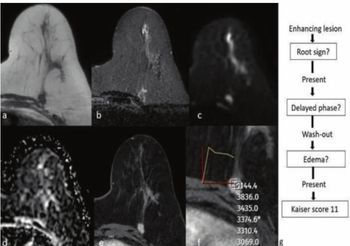
“The BI-RADS lexicon provides descriptors and assessment categories for lesions, but it does not offer precise rules on how to manage lesions with particular features. The (Kaiser score) can fill this gap. … In our study, the utilization of the KS significantly improved performance compared to using a single BI-RADS for CEM and MRI,” wrote Bei Hua, M.D., who is affiliated with the Department of Radiology and Nuclear Medicine at the First Hospital of Hebei Medical University in Shijiazhuang, China, and colleagues.
The study authors also noted comparable AUCs for KS-MRI (87.6 percent) and KS-CEM (87.8 percent). The use of KS-CEM had an 83.19 percent rate of characterizing irregular lesion margins in cases of malignancy in comparison to 89.16 percent for KS-MRI, according to the researchers.
“CEM could increase the detection rate and decrease the misdiagnosis rate, with a diagnostic efficiency similar to that of breast MRI. In our study, the detection rate of the root sign and margin in CEM was similar to that in MRI. We found that CEM had similar efficiency to MRI in observing the morphological features of breast masses,” noted Hua and colleagues.
Three Key Takeaways
1. Higher specificity on CEM with Kaiser score. The machine learning-derived Kaiser score (KS) demonstrated higher specificity compared to BI-RADS for contrast-enhanced mammography (CEM) with 69.72 percent specificity in compared to 39.47 percent for BI-RADS.
2. Improved specificity with KS-MRI. While BI-RADS MRI showed higher sensitivity (96.55 percent vs. 91.23 percent) and negative predictive value (NPV), KS-MRI significantly outperformed BI-RADS MRI in specificity (67.57 percent vs. 51.43 percent) and exhibited higher positive predictive value (PPV). This suggests that KS-MRI may reduce false positives and provide a more accurate diagnosis in cases where specificity is crucial.
3. Comparable AUC for CEM and MRI. The study authors found that the KS performed similarly for both CEM and MRI in the subanalysis with areas under the curve (AUC) of 87.8 percent and 87.6 percent, respectively, indicating that CEM may offer diagnostic efficiency comparable to MRI for breast cancer detection.
However, the researchers pointed out some differences between KS-MRI and KS-CEM with respect to KS-MRI’s higher detection of IEP as well as differences with the modified time-intensity curve (mTIC) with KS-CEM and the TIC with KS-MRI in the distribution of type 1 and type 2 lesions.
The researchers suggested that the mTIC and TIC differences may be attributed to possible differences in the pharmacokinetic makeup of iodine used for CEM and gadolinium employed for MRI, different positioning of the region of interest (ROI) and more detailed TIC plotting with MRI in contrast to CEM.
(Editor’s note: For related content, see “Enhancing Lesions on Breast MRI: Can an Updated Kaiser Scoring Model Improve Detection?,” “Multicenter Study Identifies Key Factors Associated with Mammogram-Occult Ipsilateral Breast Cancer” and “Study: Contrast-Enhanced Mammography Offers Significantly Higher Sensitivity for Breast Cancer in Dense Breasts.”)
Beyond the inherent limitations of a single facility study, the researchers acknowledged the small cohort size and conceded that non-enhancing lesions prohibited identification of TIC type and internal enhancement pattern, two of the five common features utilized for the Kaiser score. The study authors noted that women with non-enhancing lesions and non-mass enhancement (NME) lesions were excluded from the study. The researchers also pointed out they did not assess the potential impact of lesion size and background parenchymal enhancement (BPE) on the study results.