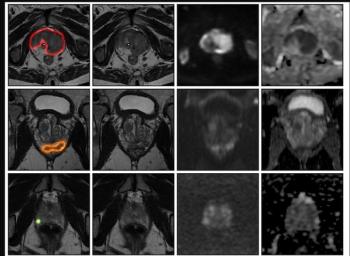
“The (AUC for positive target of MRI) was between age and f/tPSA, its sensitivity was less than age and its specificity was less than f/tPSA. This might be related to the superior diagnostic ability of MRI for intermediate and high-risk PC than for low-risk PC,” wrote lead study author Ling Zhou, M.D., who is affiliated with the Department of Ultrasound in Medicine at Sir Run Run Shaw Hospital and the School of Medicine at Zhejiang University in Zhejiang, China, and colleagues.
A predictive model that combined all three independent factors for GGG upgrading demonstrated a 15 percent increase in sensitivity over age (79.7 percent vs. 64.6 percent). Researchers also noted a higher AUC (75.1 percent) and accuracy rate (70 percent) for the combined predictive model in comparison to the individual predictive factors but also noted a specificity rate (60.5 percent) that was significantly lower than that for f/tPSA and positive target of MRI.
Three Key Takeaways
- Positive target of MRI as a significant predictor. The study indicates that a positive target of magnetic resonance imaging (MRI) is a crucial factor in predicting the upgrading of prostate cancer risk after a radical prostatectomy (RP). Patients with a positive target of MRI had a slightly greater than threefold increased risk for Gleason Grading Group (GGG) upgrading of prostate cancer risk.
- Independent predictive factors. In a multivariate analysis, the researchers identified three independent predictive factors for post-radical prostatectomy upgrading: age, free/total prostate-specific antigen (f/tPSA), and positive target of MRI. Study authors did note differences in sensitivity, specificity and accuracy rates for these predictive factors.
- Combined predictive model for improved sensitivity. Combining all three independent factors (age, f/tPSA, and positive target of MRI) in a predictive model demonstrated a 15 percent increase in sensitivity over age alone. While this combined model showed higher sensitivity, it also had a lower specificity rate compared to individual predictive factors, suggesting a trade-off between sensitivity and specificity in predicting GGG upgrading.
For each increased level of GGG, the study authors noted increasingly higher proportions of patients with increased age and positive target of MRI.
“On the one hand, the increase in tumor aggressiveness (for elderly patients) aggravated the destruction of the epithelial cell barrier, resulting in increased PSA concentration into the blood; on the other hand, the rapid proliferation of tumors led to more typical malignant features on MRI images. In addition, the postoperative GGG in the upgrading group was mainly grade 2 or 3, indicating that the imaging findings of some intermediate-risk PC patients were not typical,” noted Zhou and colleagues.
The researchers also suggested that inaccurate positioning with the CEUS positive target may have contributed to the modality’s lower sensitivity and accuracy rates in comparison to those of the MRI positive target.
“If high-grade tumors account for a relatively low proportion of positive targets, or if the GS difference between the upgraded high-grade tumors and the low-risk tumors in biopsy specimens is small, CEUS alone was difficult to distinguish high-grade PC, resulting (in) biopsy results of positive targets (that) might not necessarily obtain the highest GS,” added Zhou and colleagues.
(Editor’s note: For related content, see “Multinational Study Suggests High Variability with Quality of Prostate MRI,” “Can Pre-Op MRI Staging Help Predict Prostate Cancer Recurrence After a Prostatectomy?” and “Emerging Predictive Model with mpMRI Findings May Reduce Up to 43 Percent of Unnecessary Systematic Prostate Biopsies.”)
Beyond the inherent limitations of a single-center retrospective study, the researchers noted a relatively small sample size and the loss of partial study samples due to a lack of comprehensive collection for some of the indicators evaluated in the study.