“The findings suggest that key PCI planning decisions can be shifted from the cardiac catheterization laboratory to pre-procedural CCTA, thereby extending the role of CCTA beyond diagnosis. … By defining coronary anatomy, disease complexity, and the anticipated benefit of revascularization in advance, CCTA may allow patients and clinicians to discuss treatment alternatives, expected benefits, and procedural risks before cardiac catheterization,” noted lead study author Carlos Collet, MD, PhD, who is affiliated with the Cardiovascular Research Foundation in New York, and colleagues.
Does CCTA Guidance Facilitate Shorter PCI Procedures?
The researchers also noted a shorter duration of PCI with CCTA guidance in comparison to IVUS guidance (46 minutes vs. 63 minutes).
“The reduction in the duration of PCI merits consideration because advanced calcium-modification devices were used more commonly in the CCTA-guided PCI group than in the IVUS-guided PCI group (in 9.2% vs. 3.8% of the patients); procedures involving these devices generally require additional steps and may prolong catheterization-laboratory time,” pointed out Collet and colleagues.
Three Key Takeaways
• CCTA guidance was noninferior to IVUS for one-year outcomes. In 1,105 patients with physiologically significant disease (CCTA-derived FFR < 80 percent and at least one lesion with > 70 percent stenosis), target vessel failure at one year was 4.1 percent with CCTA-guided PCI and 4.6 percent with IVUS-guided PCI.
• Procedures were shorter with CCTA guidance. Median PCI duration was 46 minutes with CCTA versus 63 minutes with IVUS. This held even though advanced calcium-modification devices were used more than twice as often in the CCTA group (9.2 percent vs. 3.8 percent), and those devices usually add procedural steps.
• Planning can move ahead of the cath lab, but there may limits in generalizability with the CCTA-guided approach. Pre-procedural CCTA can define anatomy, lesion complexity, device needs, and expected revascularization benefit in advance. That supports shared decision-making with patients before catheterization. Caveats with the study included a high use of guideline-directed medical therapy that may have affected reported event rates and limited representation of women (comprising 21.7 percent of the cohort).
Can CCTA Guidance Enhance PCI Procedure Planning?
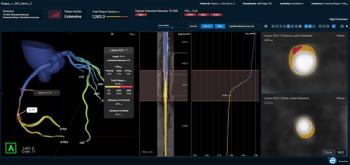
By combining pre-op anatomical and physiological evaluation with intra-procedural guidance and stent optimization, CCTA guidance may facilitate key advantages in PCI planning prior to patients undergoing catheterization procedures, according to the study authors.
“ … Information used to plan PCI can, in appropriately selected patients, be obtained before catheterization and incorporated into a procedural strategy. This approach may be increasingly relevant as the use of CCTA before invasive angiography expands. CCTA allows operators to anticipate complexity and procedural requirements before catheterization,” emphasized Collet and colleagues.
(Editor’s note: For related content, see “Study Shows Merits of CTA-Derived Quantitative Flow Radio in Predicting MACE,”“FDA Clears AI-Enabled FFR-IQ Software for Estimating Fractional Flow Reserve from CCTA” and “What New CCTA and Deep Learning Research Reveal About Small Plaque Volume and Coronary Atherosclerosis.”)
In regard to study limitations, the authors cautioned that high use of guide-directed medical therapy in the cohort and patient selection based on coronary physiological information may have affected the reported incidence rates for target-vessel failure. They also acknowledged that women comprised only 21.7 percent of the cohort.