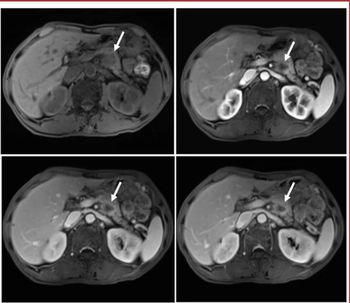
“MRI-based surveillance overcomes these (semiannual ultrasound exam) limitations with evidence supporting its superiority for early-stage HCC detection. Full-sequence gadoxetic acid-enhanced MRI provides a hepatobiliary phase with excellent tissue contrast, achieving the highest sensitivity for HCC detection, particularly of small lesions,” noted lead study author Byeong Geun Song, MD, who is affiliated with the Department of Medicine at Samsung Medical Center and the Sungkyunkwan University School of Medicine in Seoul, Korea, and colleagues.
Three Key Takeaways
• Risk-stratified MRI surveillance detects HCC earlier than ultrasound. Nearly 77 percent of cancers were caught at very early stage (<2 cm) with risk-adapted MRI, versus a pooled sensitivity of only 47–63 percent reported for semiannual ultrasound in prior meta-analyses.
• Risk-adapted MRI surveillance can lead to fewer exams than fixed semiannual ultrasound. Rather than scanning every patient every six months, intervals were tailored by risk (3–36 months), cutting total exams by 44.2 percent (237 vs. 425) compared to uniform semiannual monitoring. Researchers reported no surveillance failures, suggesting that less frequent, risk-targeted MRI can outperform more frequent, one-size-fits-all ultrasound monitoring.
• Gadoxetic acid-enhanced MRI's hepatobiliary phase may play a key role in the diagnostic gains. The study authors suggested that the excellent tissue contrast this contrast agent provides in the hepatobiliary phase may have facilitated high sensitivity for small lesions.
Could Risk-Stratified MRI Surveillance Reduce the Number of Exams for HCC Monitoring in Patients with Cirrhosis?
In comparison to semiannual ultrasound exams for HCC monitoring in patients with cirrhosis, the study authors also found that the use of risk-stratified MRI surveillance reduced surveillance exams by 44.2 percent.1
“This approach enables efficient surveillance resource allocation, intensifying follow-up for high-risk patients while safely extending intervals for low-risk patients. Therefore, this risk-adapted strategy is particularly advantageous when applying resource-intensive modalities such as MRI for HCC surveillance in high-risk populations,” emphasized Song and colleagues.
(Editor’s note: For related content, see “Predicting Microvascular Invasion in HCC: What a New Meta-Analysis Reveals About MRI and Ultrasound,” “Interventional Radiology in Focus: A Closer Look at Y90 Radioembolization for Patients with Liver Cancer” and “MRI-Based AI Models Show Significant Decline in External Validation for Pre-Op Prediction Grading of HCC.”)
In regard to study limitations, the authors noted it was a single-center study with a relatively small cohort and that all MRI exams were evaluated by one experienced radiologist. The researchers acknowledged that the cohort was drawn from a Korean tertiary referral hospital with patients having compensated cirrhosis of viral etiology. The study authors also pointed out that over 16 percent of the original cohort were lost to follow-up.
References
- Song BG, Jeong WK, Goh MJ, et al. Risk-stratified MRI surveillance for hepatocellular carcinoma in cirrhosis: a prospective cohort study. Eur Radiol. 2026 Aug 15. doi: 10.1007/s00330-026-12820-0.
2. Tzartzeva J, Obi J, Rich NE, et al. Surveillance imaging and alpha fetoprotein for early detection of hepatocellular carcinoma in patients with cirrhosis: a meta-analysis. Gastroenterology. 2018;154(6):1706-1718.
3. Singal AG, Zhang E, Narasimman M, et al. HCC surveillance improves early detection, curative treatment receipt, and survival in patients with cirrhosis: a meta-analysis. J Hepatol. 2022:77(1):128-139.